


To read the full story click here.
News

Congratulations to Katherine Gergen Barnett and co-authors for the publication of their article”Warm Handoffs and Attendance at Initial Integrated Bahvioral Health Appointments” in the peer review research journal Annals of Family Medicine.
Click here to read the full story.

Congratulations to Brian Penti and co-authors for the publication of their manuscript “The Role of the Physician When a Patient Disclosures Intimate Partner Violence Perpetration: A Literature Review” in the Journal of the American board of Family Medicine.
Click here to read the full article and press release.
 Congratulations to Suzanne Mitchell who is first author of this important paper from the national PCORI funded Project Achieve research group!
Click below to see Dr. Mitchell’s paper and press release!
Mitchell ACHIEVE Focus group paper

Dear DFM faculty, residents and staff,
It is my pleasure to announce that Jeff Markuns MD, EdM has recently been hired in a new role as the Deputy Director of the Primary Health Care Performance Initiative. Jeff will carry out this new role from the BU-DFM and remain on the faculty. The PHCPI is a Gates Foundation-funded program bringing together the World Health Organization, the World Bank, Ariadne Labs and Research for Development in a consortium committed to developing new indicators and ways of measuring primary health care in low and middle income countries, and more generally promoting primary health care as a major agenda item for all institutions involved in global health. Over the next few months, the PHCPI will be launching a Vital Signs Profile for measuring primary health care systems in low income countries, supporting its use in several exemplar countries, and working alongside the WHO in promoting activities related to the upcoming 40th anniversary of Alma Ata.
Jeff will now be able to bring his considerable experience developed here at BU in global primary care systems strengthening and Family Medicine development to a worldwide stage. Jeff is “thrilled to have this opportunity to work together with such influential partners on a global scale in bringing the new U.N. Sustainable Development Goal for Health to reality: Ensure healthy lives and promote well-being for all at all ages.” Jeff will also continue leading our successful Global Health Collaborative in the DFM as well as BU’s Health Sciences Education Masters and Certificate program here in GMS.
Jeff’s selection for this position is a testament to the remarkable work achieved here in the BU/BMC DFM in global health related to primary care. Please join me in offering congratulations to Jeff on this exciting transition, and I encourage all of you to follow the work of the PHCPI in the coming months (www.phcperformanceinitiative.org).
Sincerely,

Congratulations to Paula Gardiner and her co-authors in the DFM — Katherine Gergen Barnett, Brian Penti, Rob Saper, Pam Adelstein, Ivy Brackup, Christine Farrell-Riley, Lance Laird, and Suzanne Mitchell – for publication of their important article article “Design of the integrative medical group visits randomized control trial for underserved patients with chronic pain and depression” that was published in Contemporary Clinical Trials.
Click the link provided to read the full provider: Published IMGV RCT Methods Paper.
Congratulations to Jeff Markuns, MD, MEd for getting his article “Development and validation of the Vietnamese primary care assessment tool”published!
 Congratulations to Jeff Markuns, MD, MEd for publication of the important article “Development and validation of the Vietnamese primary care assessment tool” in which he and his colleagues adapted the PCAT Primary Care Assessment Tool for Vietnam. This work will allow formal assessment of the rapidly growing family medicine sector within Vietnam that Jeff and his team have been so involved with for many years.
Click here to read the full article!
The Hero of Preconception Care
BOSTON – Health care might have found its Wonder Woman. She can identify health risks in young African-American women and help them successfully resolve those risks. She is engaging, empathetic, culturally competent, and extremely knowledgeable in preconception care. And soon, her advice will be available at any time to participants in a new study at Boston Medical Center meant to overcome factors that are detrimental to black women’s health, like limited physician time and resources.
She can also be everywhere at once because Gabby, a significant healthcare disruptor, is not a real, physical person. The Gabby Preconception Care system, her formal name, is an embodied, online animated character, delivered via computer or tablet screen. She is programmed and designed to screen young black and African-American women for more than 100 general and reproductive health risks and to help them resolve those risks for before pregnancy.
“Gabby is part of a new effort to focus on engaging young women before they become pregnant – a concept called preconception care,” said Brian Jack, MD, chief of family medicine at Boston Medical Center. “Essentially, healthy women are more likely to have healthy babies.”
Despite decades of research, health disparities in birth outcomes persist for black and African-American women, who are more than two times as likely to deliver a low-birth weight infant as white women. Intervention studies in prenatal care have not been shown to lessen persistent disparities in birth outcomes, and it may be too little, too late in attempts to resolve concerning health disparities. In addition, there has been only modest progress in implementing what is known about preconception care into clinical practice, and little research has been done to translate preconception care knowledge into health delivery systems.
Jack’s team has spent the last six years developing, refining, and studying Gabby to fill that delivery gap in preconception care. She represents a prototype for the future of health care delivery by aligning with current technology and supplementing the care provided by community-based health providers.
Gabby faces her next test in real-world clinical settings at six Healthy Start and six Community Health Center sites. The new study, which is supported by a $1.58 million grant from the Agency for Healthcare Research and Quality (AHRQ), will recruit 60 black or African-American women to interact with Gabby over six to nine months – at times decided by users.
Gabby has been successful in her mission to reduce pregnancy health risks before. In a randomized control trial, Gabby identified and successfully resolved health risks by more than 25 percent compared to a control group. Almost two-thirds of participants in the trial reported they used information from Gabby to improve their health, and another 22 percent planned to do so in the future.
“Gabby’s ability to deliver content in a simple, conversational style is the closest person to person communication a device can provide. Her nonverbal conversational behaviors also enhance recall of critical information, as education is the key to the Gabby System and mitigating health risks,” said Jack, who is also a professor and chair of the department of family medicine at Boston University School of Medicine.
The content of the Gabby system is tailored to women’s desired outcome and is based on the Centers for Disease Control and Prevention “Content of Preconception Care.” For example, Gabby can tell the difference between women who are interested in pregnancy prevention versus women who want to become pregnant. Gabby delivers specific health behavior change dialogue using techniques like motivational interviewing and shared decision making.
Subjects in the study will be able to create a “My Health to-Do List” during and after their interactions with Gabby, which they can share with their medical providers. Post study, Jack plans to release an implementation toolkit to facilitate broader dissemination of Gabby.
“The Gabby System is designed to extend the patient-provider conversation beyond the office,” Jack said. “Gabby won’t replace the interaction between patients and providers, but instead serves as a catalyst for discussions between them. She’s another resource that can be offered by providers to ultimately facilitate the invaluable, and often time-consuming work clinicians intend to accomplish with their patients, but do not always manage to do so.”
More information on the Gabby System and study grant can be found on AHRQ’s website.
About Boston Medical Center
Boston Medical Center is a private, not-for-profit, 487-bed, academic medical center that is the primary teaching affiliate of Boston University School of Medicine. It is the largest and busiest provider of trauma and emergency services in New England. Committed to providing high-quality health care to all, the hospital offers a full spectrum of pediatric and adult care services including primary and family medicine and advanced specialty care with an emphasis on community-based care. Boston Medical Center offers specialized care for complex health problems and is a leading research institution, receiving more than $117 million in sponsored research funding in fiscal year 2016. It is the 13th largest recipient of funding in the U.S. from the National Institutes of Health among independent hospitals. In 1997, BMC founded Boston Medical Center Health Plan, Inc., now one of the top ranked Medicaid MCOs in the country, as a non-profit managed care organization. It does business in Massachusetts as BMC HealthNet Plan and as Well Sense Health Plan in New Hampshire, serving 290,000 people, collectively. Boston Medical Center and Boston University School of Medicine are partners in the Boston HealthNet – 14 community health centers focused on providing exceptional health care to residents of Boston. For more information, please visit http://www.bmc.org.
Boston Student Selected for Family Medicine Leads Emerging Leader Institute Jin is one of 30 Participants
 Boston, MA- Helen Jin is one of just 30 scholarship winners nationwide selected to participate in he Family Medicine Leads Emerging Leader Institute. Jin is a 4th year medical student at Boston University. As a scholarship winner, Md. Jin will participate in a year-long leadership development program.
The Family Medicine Leads Emerging Leader Institute is a program of the American Academy of Family Physicians Foundation. It is funded by family physician donors and aims to identify and train Family Medicine residents and medical students who have leadership potential, but may not yet have served in a major leadership role.

Check out the article “Patients Cared For By Female Doctors Fare Better” written by Sarah Anne Schumann from DFM’s first residency class. Click here to read the full story.

DFM’s Holiday Party at the House of Blues was a great success! Click here to watch our fun montage of photos put together by our very own Doria from the holiday party. Thank you, Doria!

Congratulations to Katherine Gergen Barnett for being mentioned in the article “Restored Health Renews Purpose for Elizabeth”. Click here to read the full story.

Congratulations to Paula Gardiner, MD, MPH for her published article “Current State of Child Health in Rural America: How Context Shapes Children’s Health”.
This purpose of this essay is to provide a detailed description of the status of children in rural America to highlight features of the rural environment that may affect health. Click here to read the full article.
 Relational Practices in Health and Healthcare: Healing through Collaboration
By: Katherine Gergen Barnett, MD
What does relational health and healthcare mean to you?
Health in healthcare cannot happen without the power of the relationship. Traditionally, this has been about the connection between the provider and patient. Developing this relationship is a timeless art – one that is built on fostering curiosity, true listening, empathy, and understanding. Many of us spend our lives teaching these skills to medical students, residents and practicing doctors. However, in our increasingly complex world of medicine, relational health is beyond the matrix of the clinician- patient and spans to include relationship to other patients, relationships to other providers on the medical team, and relationships to community resources. Medicine is now moving to team based care where we have social workers, psychiatrists, pharmacists, nurse practitioners, practice assistants, nurses, patient navigators and care management members on our teams. Each of these individuals serves a critical role in bringing a patient to health. Group medical visits give a chance for patients to connect to others suffering from the same conditions and those relationships are part of their healing. Finally, health is created and strengthened when individuals are connected to resources within their community- getting locally sources foods at CSAs (Community Supported Agriculture) , exercising at the local Y, walking on safe sidewalks, biking in safe bike lanes, having safe affordable child care, etc. Healthcare is moving in a very exciting direction where increasingly we are getting government incentives to turn health care delivery in a much more relational way. This is what gets me excited every day in the work at Boston Medical Center, New England’s largest safety net hospital.
Can you share an example?
See the Integrative Medicine Group Visits paper. (Click here). Also happy to share more!What’s is one practice that you think could transform the future of healthcare?
Group medical visits and, if I had to name another, greater utilization of community health workers.How might we spread the ideas and practices of relational health and healthcare?It is incredibly exciting to have the Taos Institute focusing on Relational Practices in Healthcare in their upcoming conference. Part of what needs to be done is better communications across all sectors – Community health Workers, social workers, nursing, community organizers, doctors, etc. so that we can be in greater dialogue about what each of us is doing in the field of relational health (using language so that each sector can better understand what this means). So many of us are moving in the same direction but are working in siloes. If we all got on the same page and actually starting building on each other’s work and dialoguing, we could move the field of health forward at greater leaps and bounds. After all, no healing can be done outside of the context of relationships.
Click here to go to the website.

Congratulations to Suzanne Mitchell for being quoted in the Kaiser Health News story “How to Fight for Yourself at the Hospital- And Avoid Readmission” (click here to read the full story) and in the Daily Herald in the story “Don’t leave the hospital until you know comes next” (click here to read the full story).
.
Click here to read the full story.

Alysa Veidis
Associate Medical Director, Family Medicine at Boston Medical Center
EDUCATION: Boston College (Chestnut Hill, MA), Northeastern University (Boston, MA)
Alysa Veidis, MSN, RN, FNP-BC, has been appointed by MA Governor Charlie Baker to serve on a special commission examining the feasibility of establishing a pain management access prive treatment options.
Click here to see this story in the Boston Business Journal.
Check out Katherine Gergen Barnett in the BMC Video “Patience Experience Forum: Improvements”
Chair Column April 26, 2016
To the DFM Faculty, Residents, Staff and Friends of the Department,
In this edition of the DFM Newsletter, I would like to highlight the value of our relationship with the Boston HealthNet Community Health Centers. CHCs are an important part of health reform. Across the US, 1,400 CHCs create a safety net for over 24 million patients. But challenges remain. Manny Lopes, CEO of East Boston Neighborhood Health Center points out at a recent National Association of CHCs (NACHC) meeting that recruitment and retention of clinical providers remains an issue.
Click here to read a supporting article:
The March issue the NACHC newsletter reports that almost all health Centers (95%) are experiencing at least one clinical vacancy today. The positions that CHCs report to be most commonly vacant are those for family physicians. More than two-thirds of health centers indicate that they are currently recruiting for at least one family physician!
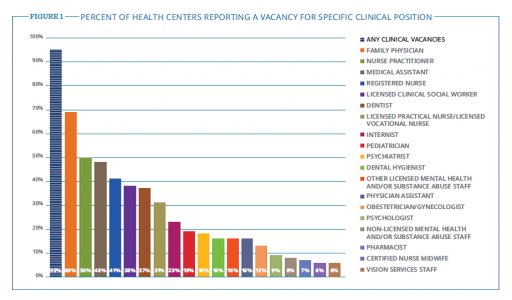
Our Boston HealthNet–BU Department of Family Medicine collaborative is working together to successfully recruit to our CHCs the kind of doctors America needs. I am proud to report that 6 of the 10 of residents in our graduating class this year are staying within the Boston HealthNet CHCs this year. They will be working at Mattapan CHC (2), South End CHC, Codman Square CHC, East Boston NHC, and BMC FM. Over the past 16 years, now 60% of all our 103 graduates have chosen to work in the BHN CHCs or in the DFM [link to the slide below] and the retention of these graduates is remarkably high.

Finally, elsewhere in this edition of the newsletter is an announcement of the first year residents who will be joining our program in June. You will notice that we now have expanded to 12 residents per year – and we are very proud that this group of newly matched BMC Family Residents — who are 50% underrepresented minority students – begin to looks like the community we serve.
By these measures, this is the most successful teaching CHC – academic health center alliance in the US – benefiting the people of Boston. This is something for which we should all be proud.
-Dr. Brian Jack

Hilton Minneapolis Downtown
Minneapolis, Minnesota
April 30-May 4, 2016
Presentation schedule: DFM Brochure STFM Annual_42116
Coming of the Light: The 2015 Integrator Top 10 for Policy and Action in Integrative Health and Medicine
#3. Katherine Gergen-Barnett, M.D. and Integrative Medicine Group Visits at Health Affairs
“Meanwhile, at the safety net Boston Medical Center, Katherine Gergen-Barnett, M.D. (pictured), a researcher associated with Paula Gardiner, M.D., MPH’s PCORI grant on integrative medicine group visits, broke through a rarely-crossed publication barrier with a paper on integrative medicine group visits in the powerfulHealth Affairs. It is long-past time to put these group-delivered services into the center of integrative education and practice.”
To read the full story click here.
Ground-Breaking Research on Integrative Medicine that may Help People Living with Chronic Pain
Guest: Dr Katherine Gergen Barnett
Presenter: Wayne Bucklar
Guest Bio: Dr Katherine Gergen Barnett is the Director of the Integrative Medicine Clinical Services at Boston Medical Centre where she also serves as a primary care clinician. Dr. Gergen Barnett attended Yale University School of Medicine. As a medical student, she worked at the National Centre for Complementary and Alternative Medicine at the National Institute for Health, studied holistic medicine with Dr. Andrew Weil, lived on a pueblo/reservation, created a course for medical students on spirituality and medicine, and completed a fellowship studying a model of group prenatal care. Her primary interests are preventive medicine, nutrition, mindfulness-based stress reduction, women’s health, and group care.
Segment overview: In today’s Health Supplier Segment, let us welcome Dr Katherine Gergen Barnett the keynote speaker for this year’s Blackmores Institute Symposium. Health practicioners attending the said symposium this month will learn more about the field of integrative medicine and the use of specific integrative medicine modalities in the United States. She will frame the data in the context of health care delivery in the United States, specifically how Integrative Medicine is still considered a set of modalities available and accessible only to patients with monetary means. Dr. Gergen Barnett will also detail how her program at Boston Medical Center is providing high quality evidence based integrative medicine care to the urban poor. She will also discuss lessons learned as well as its implications for the future promise of integrative medicine globally.
Transcription
Health Professional Radio
Wayne Bucklar: You’re listening to Health Professional Radio with Wayne Bucklar. My guest today joins us from Melbourne, Australia where she is visiting from Boston in the United States. It’s Dr. Katherine Gergen Barnett and she is the Director of the Integrative Medicine Clinical Services at Boston Medical Center. Katherine’s first trip to Australia, welcome to Australia Katherine.
Dr. Katherine Gergen Barnett: Thank you so much Wayne. I’m so thrilled to be here. And thank you for having me today.
W: Now I understand you’re here as the keynote speaker for this year’s Blackmores Institute Symposium, which is this week I think?
K: That is correct, yeah. The Blackmores Institute Symposium is this weekend and I’ve been very honored to present to them some of my research my colleagues and I are doing at Boston Medical Center on the treatment of chronic pain.
W: Now Katherine integrative medicine is not something I’m familiar with, but that’s not unusual because I’m not much of a clinician at all I’m afraid. Is that what you’re going to be talking about?
K: So let me just backup by saying you’re not alone and knowing so much about integrative medicine is a new in some ways a new field but certainly a growing field although it really draws upon many ancient traditions. Some of which are in the instance of traditional Chinese medicine over 2000 years old. So it’s really a study of medicine and a practice of medicine that brings in evidence based modalities both in the western medicine tradition such as pharmaceutical, surgery etc., as well from the other traditions such as “Ayurveda and traditional Chinese medicine and some Indian medicine.” Really to bring health and wellness to our patients in safe and effective means. And what I will be speaking about the conference during the keynote is really some of where we’ve gotten our current state of medicine today which is very much as we all know for anybody who has either been a patient or a practitioner, one that is largely burdened by chronic illness. WHO has put out many reports recently showing that the rates of Communicable Disease, ones that we’ve known for a long time are happily declining worldwide but our rates of chronic illness are going up at a rapid cliff. And the way that we have practiced medicine in traditional western medicine is excellent in so many ways and has really been a God sent in terms of treatment for communicable diseases, but in terms of treatment of chronic illness we know that we actually lack some of the tools to help people in a true kind of underlying way, and not just treating the symptoms but looking at some of the causes that maybe going on for some of the chronic illnesses and addressing those things. And again it’s no fault of any practitioner, that’s the way our system is set up. But an integrate medicine we’re really looking at mind body, spirit and how we can use all three of these things to get the person to propel to greater wellness.
W: Now Katherine as soon as you mentioned spirit, in many clinical circles it’s a degree of cynicism – your work is research based I understand?
K: Yes, yes thank you for clarifying. Yes, it’s everything we do is based on evidence in medicine. We’re very heavy research based group, we have grants from the NIH and from Federal Funding and what we’re doing in terms of your “spiritual” really looking at something called “mindfulness.” We just had a tremendous amount of literature and research behind it in terms of looking at some of these efficacies within chronic pain, and depression, cardiovascular disease. But really what we’re doing is again integrating those modalities into a larger medical setting. And so for instance with our care for people with chronic pain which is one of the main focuses of my talks at Blackmores Institute as speaker, we’re looking at how we can treat people with chronic pain using some of the integrative medicine approaches, but also really be looking at other thing such as you know –are there nutritional deficiencies that happening with our patients. Are there ways that we can kind a both through their health through things such as making inflammatory diet? Can we bring in their primary care physicians to treat them with different kinds of medication? And are we able to decrease some of their sequelae of chronic pain, such as depression by being in a group visit setting? Such as that they get support from other patients who are suffering from chronic pain and they know that they’re not alone and that actually goes a long way in decreasing their pain and suffering.
W: Now Katherine just for some of our audience who are not familiar with the American system, NIH that’s the funding body you mentioned, what is that body?
K: So that’s the National Institute of Health. That’s very well regarded collection of researchers based down in Maryland the Washington DC area that has the largest amount of federal dollar funding. And they give a number of grants through they have many different kind of branches study and they’ve given number of grants and scope procedures to get grants from them. And they’ve done tremendous work in advancing the research field on all levels of medicine.
W: Thank you for clarifying that for me.
K: Yes, thank you.
W: Given that you’re here talking about your research in pain management through this integrative approach, I assumed you’ve got some results that are fairly positive.
K: Yes, thank you for asking. So we’ve actually our group, our approach to chronic pain is called “Integrative Medicine Group Visits.” And the setup is such that a patient meet for 9 weeks in a group of up to 12 patients for 2 and half hours per session. And in that time as I shared with you many different modalities and the first set of data that we got after several years of running the group is that we had enormous reduction in pain, symptomatology we had reductions in depression, we had improvements complete, we had a reduction in perceived stress. And so our results were able to carry us forward into earning a very prestigious grant, again federally funded something called PCORI which is a patient center grant that Obama and this Affordable Care Act they are very focused on patient centered outcome. They granted us a $1.8 Million grant and look at our standard of care versus our intervention, and to see what the comparison was for our intervention with this standard of care for our patients. And so we’re currently 2 years into that study and that we haven’t published the outcomes, it’s continuing to be very exciting, very assurance in terms of the reductions in a lot of the most bothersome symptoms for people.
W: You’re listening to Health Professional Radio, my name is Wayne Bucklar. And my guest today is Dr. Katherine Gergen Barnett. Katherine is the Director of the Integrated Medicine Clinical Services at Boston Medical Center. And she is here in Australia to speak at the Blackmores Institute Symposium this week as the Keynote Speaker. Katherine many of our audience are clinicians, about 95% of them in fact are doctors, nurses, allied health professionals either in acute care or a lot in aged care. What message would you like them to take away from having heard you today?
K: So I just want us all to be able to think a little bit outside of the box in terms of taking care of our large numbers of people living with chronic pain. In Australia it’s 1 in 5 people below the age of 65. And once you get greater than 65, it’s 1 in 3 and these are very parallel in the US. And through the messages of speaking about the whole person in what you can do to improve not only treat their symptom of pain but perhaps get a little bit deeper into some of the causes of their pain. And it’s not all about fixing but rather sometimes it’s about doing, some of those causes.
W: Getting clinicians to think outside of the box is never a quick process into the health industry.
K: (giggle)
W: But I’m sure there’ll be some who’d be very interested to hear what you have to say and what you’d be saying on the weekend. Is there a common misconception about your work that drive you nuts and keep you awake at night?
K: I wouldn’t say very much keeps me awake at night, since I have 3 young children and I work full time.
W: (Laugh)
K: But I will tell you that I think this is changing happily because of the quality of research that is being done in this field, including ours at Boston Medical Center and many others in the US and the Blackmores Institute here. But I think that for me it’s really making sure that we are putting together good studies, and that we’re publishing our study so that all of us as scientific clinicians can really work together and look at the evidence, wipe away some of our biases and really look at what’s best for the patient.
W: Well let’s hope today that we can address that misconception with perhaps just a few, but will do our best. Katherine it’s been a pleasure having you on with us today. Thank you for making the time available.
K: Thank you so much Wayne. It’s an honor to do this work and to speak with you today about it.
W: If you just joined us, you’ve just missed my conversation with Dr. Katherine Gergen-Barnett who’s here for the Blackmores Institute Symposium this weekend from her regular job as the Director of Integrative Medicine Clinical Services at Boston Medical Center obviously in the US. The good news however is that on our website we have a transcript of my conversation with Katherine, we also have an audio archive on both SoundCloud and YouTube so do head off to our website at www.hpr.fm. You can check at either the audio or the transcript. My name is Wayne Bucklar, you’re listening to Health Professional Radio.
To hear interview click here.
League Celebrates 50th Anniversary of Nation’s First Health Center; Looks to Future of Community-Based Health
Victoria Reggie Kennedy, Mayor Martin J. Walsh, and U.S. Representatives Stephen Lynch and Michael Capuano will join national and local leaders and community health advocates for a day-long symposium to commemorate the 50th anniversary of the founding of the nation’s first community health center at Columbia Point, and to look to the future. Now serving one in seven Massachusetts residents, the community health center movement laid the groundwork for national healthcare reform and has proven that high quality care and lower healthcare costs can be achieved together.
The symposium at the Edward M. Kennedy Institute for the Massachusetts Senate will feature panel discussions on the federal government’s role in the creation and growth of health centers, how community health centers changed the model and delivery of healthcare, and 21st century workforce strategies to recruit new talent and bridge the provider gap. It will also include a speaking program with special presentations to Victoria Reggie Kennedy, the Kraft family and to Dr. H. Jack Geiger, whose vision spurred the roots of a movement 50 years ago. – See more at: http://www.massleague.org/#sthash.AvpdaONh.dpuf
To read more click here.
Halloween Fun in East Boston!

Syn demics and Legislative Outreach
Society for Medical Anthropology
Bayla Ostrach (Boston U School of Medicine)
Ashley Houston (Boston U School of Medicine)
Merrill Singer (U Connecticut)
An Experiment in Educating Congress about the Health Effects of War
Syndemics and Legislative Outreach | Anthropology-News
We often think of long-term health effects of war in terms of a legacy of suffering for combatants and people directly affected by battlefield events. Less attention is paid to the ways that war increases the burden of disease among broader populations. Little research focuses on how government policies and defense strategies such as sanctions, embargoes, and destruction of infrastructure are inscribed on the bodies not only of those who survive, but also in the illness experiences of those living in countries shaped by war, decades later. Two of us published an article in the Annals of Anthropological Practice, “Syndemics of War: Malnutrition-Infectious Disease Interactions and the Unintended Health Consequences of Intentional War Policies,” (Ostrach & Singer 2012) drawing attention to a syndemic composed of war policies that produce interactions between malnutrition and infectious diseases, to increase the overall burden of disease. Identifying a syndemic requires examining multiple diseases or biological factors that additively interact under adverse social conditions, resulting in biological interactions that would likely not occur without structural factors, and that increase suffering (Singer 2014). Syndemics illuminate mutually reinforcing layers of suffering related to biomedical, behavioral, and other health conditions that occur within and because of adverse social conditions.

Beyond Medicine: The Road From Health Insurance To Health
Congratulations to Katherine Gergen-Barnett, M.D. on the publication of her piece entitled Beyond Medicine: The Road From Health Insurance to Health.
Now that as many as 6.4 million low- and middle-income Americans across 34 states have health insurance as a result of the Affordable Care Act, it’s worth asking this question: When does health insurance turn into actual health?
It’s a legitimate question because the impact of health insurance on health has been shown to be less impressive than we might wish. At least one study out of Massachusetts, for instance, hasdemonstrated reductions in mortality associated with insurance status, while other studies out of Oregon show only modest reductions in mental health disease burden. So how much health have we really gained nationwide from the ACA’s insurance expansion? It remains to be seen.
In the meantime, it may be time to turn our collective attention to a slightly different question: Where else in Americans’ lives might we find more substantive ways to improve health?
To read more click here.
CitiMatCH 2016 Abstract
The Health Perspectives of African American Adolescents and Young Men
Leanne Yinusa-Nyahkoon, OTR/L, ScD; Fatima Adigun; Timothy Bickmore, PhD; Karla Damus, PhD, MSPH, MN, RN, FAAN; Kenneth Harris; Clevanne Julce; Justin Kramer; Jessica Martin, MPH; Steve Martin, MD, EdM; Stefan Olafsson; Michelle St. Fleur, MD, Brian Jack, MD
Click hereto read the full abstract.
Toyin Ajayi is featured in the Boston Business Journal!
 Leading from the front
Toyin Ajayi isn't afraid to roll up her sleeves while delivering care to some of the state's neediest patients.
Click here to read the article
Fertility Awareness Methods Are Not Modern Contraceptives: Defining Contraception to Reflect Our Priorities
 Kirsten Austad, Anita Chary, Alejandra Colom, Rodrigo Barillas,dDanessa Luna, Cecilia Menjı´var, Brent Metz, Amy Petrocy, Anne Ruch, Peter Rohloffa
A recent article in GHSP calls for classifying fertility awareness methods as ‘‘modern contraceptives’’ despite their inferiority. We believe in a rights-based approach, which considers the real-world conditions that many women face, including constrained sexual agency and low baseline reproductive health literacy. We must demonstrate true commitment to increasing access to the most effective and reliable contraceptive methods.
Unintended pregnancy is both a global public health challenge and an important human rights issue.1 Worldwide 40% of pregnancies are unintended.2 These unintended pregnancies pose significant health risks to women because of the obstetrical risks of multiple births, short interpregnancy intervals, and unsafe abortions, as well as because they worsen povertyrelated inequalities. Addressing this unmet need for family planning mandates a coordinated response of dedicated human resources, economic investment, and application of the best-available scientific evidence. Highly efficacious and safe methods of contraception including injectable and oral contraceptives, sterilization, and long-acting reversible contraceptives (LARCs), comprising implants and intrauterine devices (IUDs), are key to this effort.
Click here to read the full article Global Health: science and Practice
The end of residency means difficult goodbyes
 by Anne Toledo, MD
“It is easy to see the beginnings of things, and harder to see the ends. I can remember now, with a clarity that makes the nerves in the back of my neck constrict, when New York began for me, but I cannot lay my finger upon the moment it ended.”
– Joan Didion, Goodbye To All That
So it feels at the end of residency. Of course, there is a graduation date. However, the emotional jolt of starting intern year contrasts with a nebulous crawling sensation at the end. Residency seems to taper in repetitive, small appreciations that each teaching moment may be the last.
First came the final shift on inpatient medicine. I stood at the threshold of 6 West hospital floor and marveled that the sense of foreboding three years ago had given way to familiarity and, though hospitals can be quite dangerous, safety. Goodbye, 6 West.
Then my last ER shift passed. The other senior and I traded laughs over mutual flight anxiety between seeing patients, and suddenly it was over. Goodbye ER.
Click here to read the full story on KevinMD.com.
Congratulations to Michelle Dalencour, Karla Damus and Brian Jack for publication of their manuscript!
Congratulations to Michelle Dalencour, Karla Damus and Brian Jack for publication of their manuscript entitled "The future of preconception care in the United States: multigenerational impact on reproductive outcomes" that describes possible epigenetic mechanisms for disproportionate health disparities in premature and low birth weight births among Black women.
Click here to read the full article.
Brookline Resident Runs for Addiction Treatment
Brookline Resident Runs for Addiction Treatment
Dr. Katherine Gergen Barnett, a physician at Boston Medical Center, completed the Boston Triathlon this past weekend for Team BMC. 
BROOKLINE, MA – A Brookline doctor completed the Boston Triathlon over the weekend to raise money for substance abuse treatment in teens and young adults.
Katherine Gergen Barnett, a family medicine physician at Boston Medical Center, placed fourth in her division for Team BMC. The event raised approximately $15,000 for BMC's Catalyst Clinic, a primary care clinic for teens and young adults with or at risk of substance abuse disorders.
Gergen Barnett has been a primary care physician, researcher and educator at BMC for 11 years. She now serves as the vice chair of primary care innovation and transformation in the Department of Family Medicine.
Click here to read the full story.
Dealing with Stress: How to Prevent Burnout


“Caring for myself is not self-indulgence, it is self-preservation….”
Audre Lorde
Stress affects all of us at different times and in different ways. A small or moderate amount of stress from time to time can be a good thing—it can motivate us to stay focused and push through a new or difficult challenge. But when you experience a high amount of stress over a long period of time, you may end up dealing with burnout.
Burnout is a physical or mental collapse caused by stress, and creates a combination of mental, physical, and emotional exhaustion. This can happen when things at work, school, or in your personal life are out of balance and very stressful. The effects of burnout vary from person to person, but some include:
- loss of motivation,
- feelings of self-doubt, frustration, or exhaustion, and
- a lack of enthusiasm for things you typically enjoy.
There are strategies you can use to prevent burnout, however, and one of them is called self-care. Self-care, or intentionally taking actions to maintain for your physical, emotional, and mental health, is an effective way to keep yourself healthy through tough times.
Practicing Self-Care
There is no one right way to practice self-care. Self-care may mean fitting in early morning exercise for one person or curling up with a mug of tea and a favorite book for another. To figure out what your self-care practice might be, try writing a list of things that you do (or would like to do) that make you feel better, help relieve tension, or less stressed. If you’re stumped on what to write, consider these popular types of self-care:
- Eating healthy foods every day, or making a fun home-cooked meal each week
- Exercising daily, even if it’s for a short walk during lunchtime
- Getting more or better quality sleep
- Writing in a journal
- Practicing meditation, yoga, or prayer
- Spending quality time with friends and loved ones
- Setting aside time for a favorite hobby or activity
- Decreasing screen time on phones, computers, tablets, etc.
Once you have your list, break it down in to things that can be done in small blocks of time – like 15-30 minutes, an hour, a few hours, or a whole day. Keep this list somewhere where you’ll see it every day, and pick an activity that works for you that day.
Things to Keep In Mind
We are often so focused on taking care of those around us, and managing all of our responsibilities, that taking the time to practice self-care can feel strange at first. It can feel selfish or like you’re not being productive, especially since we’re taught from an early age to put the world in front of ourselves, and to always be working towards something. This can make it hard to turn off the little voice that keeps telling you to push forward and take on more – especially for women who often feel pressure to put others’ needs ahead of their own.
The beauty of self-care is that it shifts your mindset so that taking care of you becomes as much of a priority as taking care of others. When you are healthy and whole mentally, physically, and emotionally, you are in a better position to tackle problems or help others. You might need some time to get used to practicing self-care, and that’s okay! When you are in touch with your own needs, living with them in mind can help you feel happier, more open to others, and more creative.
Want to read more about this topic? Take an in-depth look at self-care and learn how it can help you here. Don't forget to leave a comment or story below!
Photograph courtesy of: http://thebodyisnotanapology.com/
Integrative Health Group Visits As Core Delivery Strategies
by John Weeks, Publisher/Editor of The Integrator Blog News and Reports
 Integrative health group visits was the topic of an April 28, 2016 grand-rounds webinar with the Academic Consortium for Integrative Medicine and Health, the organization of 68 academic medical centers promoting the integrative model. The two speakers were Katherine Gergen-Barnett, MD (pictured right) with Boston Medical Center (BMC), and Ilana Seidel, MD (pictured below) from George Washington University Medical School.
The growing exploration of “integrative health group visits” as core delivery strategies has developed from a need to consider strategies for cost savings as well as a number of other reasons including the following:
- A focus on education and empowerment in integrative health and medicine.
- Evidence that adults learn best when they are not merely being passive recipients
- The whole person philosophy that success in creating health is ultimately in the hands of the individual seeking care rather than the practitioner who provides it
 Gergen-Barnett opened the recent webinar by speaking to the power of the approach: “The idea of group visits is that we as human beings are built for community – and when we get sick we are often alone […] Group visit theory is that patients working together as a group can manage conditions better [and] not about the provider being in the room.”
Gergen-Barnett continued by explaining the group visit experience from the provider perspective: “This has been one of the most satisfying parts of my practice. Group visits take the onus off of me [as the practitioner]. In group visits, everyone is a learner and a teacher.” She went on to add that the value of these visits is more time with the patients. The sessions typically last between 2.5 and 3 hours. She also indicated that most patients have proven to be receptive to the experience. “There is a lot of evidence that even patients who are reticent about the group model come to like it.”
The webinar presentation explored two forms of group visit delivery. The first is the “closed model” that has been used at BMC and is currently the subject of a $1.8-million Patient Centered Outcomes Research Institute (PCORI) study. In this format, patients sign up for a a series of 2-3 hour visits over a period of weeks. Each billable session includes a mix of one-to-one time with an integrative professional, as well as group interactive and didactic time. The BMC model is based heavily on the Mindfulness-Based Stress Reduction format.
The other is an open model, pioneered by Jeffrey Geller, MD at the Greater Lawrence Family Health Center. In this model, patients are provided with certain times of the week that the doctor will be available and the session is shared by those who show up to participate. The model can function well with patients who face a wide variety of medical issues given the common roles of one’s relationship to stress, sleep, nutrition, mindfulness, and movement resolving or aggravating conditions.
During the webinar, Gergen-Barnett indicated that she expects even greater value and application of these methods as medical industry’s shift away from the production of services toward a “value-based” approach. Seidel echoed the opinions of Gergen-Barnett, indicating that her own experiences in practice have demonstrated that “group visits are not only good for battling loneliness but also for empowerment.”
Comment: Gergen-Barnett in particular has been championing the outcomes and the potential of the model. Her 2015 blog in the influential Health Affairs was entitled: “The Call to a New Kind of Care: Integrative Medicine Group Visits Offer Promise in the Treatment of Chronic Pain and Depression.” She spoke on the topic at the Integrative Medicine for the Underserved (IM4US.org) conference. (IM4US maintains an open source group visit resource here.) At Global Advances in Health and Medicine, Gergen-Barnett’s title was simply: “Group Visits – The Future of Healthcare.”
This is terrific work in an area in which the integrative health community should, by philosophy, be pushing the envelope. An additional resource is this posting from integrative center consultant Glenn Sabin: “4 Reasons to Consider Integrative Medicine Group Clinic Visits.”
Save the Date: Elaine Alpert MD MPH 7th Annual Lynne Stevens Speaker
 Intimate Partner Violence
Speaker: Elaine Alpert MD, MPH
Tuesday May 24, 2016
12:00 - 1:00 PM
Boston University School of Medicine
72 East Concord Street
Room L110 first floor
Attendees are cordially invited for lunch at 11:45 and
Q & A discussion from 1-2 following the lecture
Elaine Alpert MD, MPH, trained in internal medicine and public health, is an internationally-respected scholar and consultant in family violence, sexual assault, and human trafficking with expertise and experience in trauma-informed care, interprofessional and innovative educational methods, and strengthening the health sector’s role in the coordinated community response to violence and abuse across the lifespan. The Founding Chair of the Massachusetts Medical Society Committee on Violence Intervention and Prevention, Dr Alpert is the lead author of Intimate Partner Violence: the Clinician’s Guide to Identification, Assessment, Intervention and Prevention (6 th edition, 2015), as well as Human Trafficking: A Guidebook on Identification, Assessment, and Response in the Health Care Setting (2014). She has authored numerous additional important articles, guidebooks, curricula, and book chapters about family violence, sexual assault and human trafficking for physicians and other health care providers, and developed online continuing medical education about domestic and sexual violence for the Massachusetts Medical Society. She also served on the U.S. Institute of Medicine Committee on the Training Needs of Health Professionals to Respond to Family Violence
Dr. Alpert's 25-year academic career at Boston University Medical Center as a general internist, medical educator, public health faculty member, and Assistant Dean for Student Affairs, was followed in 2009 by a Fulbright Fellowship to develop and teach interprofessional courses in violence prevention and in intervention planning for improving public health at the University of British Columbia (UBC) where she served as the Director of the Interpersonal Violence Prevention Program, and created the UBC Violence Intervention and Prevention (VIP) Connector. She also continues as a consultant to the Division of Global Health and Human Rights at Massachusetts General Hospital (MGH) in Boston regarding their research and publications regarding human trafficking ,and has engaged in on-site teaching, research and/or consulting in Asia , Pacific Islands and Central America. Dr. Alpert has received honors and awards from the American Medical Association, the Massachusetts Medical Society, Futures Without Violence
The One Minute Learner: Evaluation of a New Tool to Promote Discussion of Medical Student Goals and Expectations in Clinical Learning Environments
Miriam Hoffman, MD; Molly Cohen-Osher, MD
|
BACKGROUND AND OBJECTIVES: The transition from pre-clerkship to clerkship curriculum in medical school presents many challenges to students. Student roles and supervising physicians’ expectations vary widely. Efforts to ease this transition have included third-year orientations, skills sessions, field-specific training, and peer-to-peer communication/support. We developed a new tool, called The One Minute Learner (OML), to promote and structure discussion of student goals and expectations and empower student ownership of learning. The OML can be used quickly and easily by students and faculty to facilitate integration of medical students into the clinical setting. This paper describes the OML and reports evaluation of its effectiveness through student evaluations. |
|
METHODS: We compared student responses to two end-of-clerkship questions for the academic year before the OML was implemented to the first year of implementation. Students rated their orientation to their roles and responsibility and rated the communication of what was expected of them. |
|
RESULTS: The percentage of students rating these highly increased dramatically: for “I was oriented to my responsibilities and role,” the percentage rating it highly (4–5 on a 5-point Likert scale) increased from 47% to 82%. For “Expectations of my role were communicated to me clearly” the percentage rating it highly increased from 66% to 89%. |
|
CONCLUSIONS: The OML is a new tool that can promote and structure a proactive discussion between student and teacher about goals and expectations, leading to better integration of students into the variety of clinical setting in which they rotate. |
|
(Fam Med 2016;48(3):222-5.) |
The transition to the clinical setting from the traditionally classroom-focused pre-clerkship curriculum can be difficult for medical students.1-4 Students rotate through many clinical settings; they must quickly adjust, learning their roles and what is expected of them. This can be challenging for many students3 and can cause cognitive overload, which can negatively impact their ability to focus on clinical learning.5 Prior efforts to address this include clinical-immersion courses, third-year and clerkship-specific orientations,5-7 as well as clinical skills and field-specific training.6,7 Students also use peer-to-peer communication, telling their peers about expectations, roles, the clinical environment, communication, feedback, and strategies for success.4,8,9
This paper evaluates the effectiveness of a new tool, the One Minute Learner (OML),10 that can facilitate the transition of learners into the clinical setting by promoting and structuring a proactive discussion between students and teachers about goals and expectations. It can be used in any clinical setting or specialty and with any level of learner. In contrast to prior efforts to help students integrate into the clinical setting, the OML is a discipline-neutral tool that empowers students to proactively promote these discussions with their supervisors in any clinical setting.
To continue reading click here.