What the EU’s New Compulsory Licensing Policy Signals for Global Health Governance and Flexibilities for Middle-Income Countries

By Rachel Thrasher, Deborah Gleeson, Brook K. Baker, Veronika Wirtz, Warren A. Kaplan and Brigitte Tenni
Global and regional crises call for rapid, flexible solutions, especially when it comes to access to lifesaving medicines in a health emergency. On December 30, 2025, the European Parliament published a revised regulation on compulsory licensing for crisis management. A compulsory license is a government-granted authorization to use or produce a patented product without the patent holder’s consent. This new European regulation is intended as a way to efficiently address health crises in the European Union (EU) by increasing region-wide access to “crisis-relevant products.”
Prior to this new region-wide regulation, compulsory licenses could only be granted on a country-by-country basis and were intended to meet the needs of a particular nation. The COVID-19 pandemic revealed the importance of regional coordination in the case of a wider health emergency. Beyond the narrow context of health crises, however, regional collaboration and coordination on compulsory licensing is essential to ensure sufficiency of supply and affordability of health products.
Compulsory licenses have long been a tool of intellectual property law, as a remedy for when countries decide that patent holders are not sufficiently “working” their invention or are otherwise abusing their patent rights. The World Trade Organization’s (WTO) Agreement on Trade-Related Aspects of Intellectual Property Rights (TRIPS Agreement), while placing new requirements on Member States to grant patents and other types of intellectual property protection for pharmaceutical inventions, includes a provision (Article 31) that permits Member States to adopt compulsory licensing laws within their own domestic intellectual property laws.
The right to grant compulsory licenses is among the most widely discussed “flexibilities” of the TRIPS Agreement. Member States may grant compulsory licenses in cases such as non-use of a patent, anti-competitive conduct by the patent holder, public interest needs, emergencies or for non-commercial government use (often referred to as “government use” licenses). While these rules are far from perfect, it is worth noting that a majority of the world’s countries have adopted some version of these laws.
In a recent report, researchers from the Boston University Global Development Policy Center’s Working Group on Trade and Investment Treaties and Access to Medicines explore the extent to which a selected set of middle-income countries have incorporated key provisions of the TRIPS Agreement into their own compulsory licensing laws. This research compares the language of different country laws and then measures them against a more complete list of compulsory licensing provisions that could contribute to better access to health products as best practices. While each of the countries studied had adopted some relevant legislation, they differ widely in their adoption of various beneficial aspects of those laws and could benefit from increasing certain flexibilities relevant for health.
Background of compulsory licensing use
Despite the explicit flexibility introduced under the TRIPS Agreement to issue compulsory licenses, low- and middle-income countries have long faced opposition by pharmaceutical companies and high-income countries when they attempt to deploy these tools. After a public outcry in the late 1990s and early 2000s, WTO members came together to confirm their right to grant compulsory licenses under the agreement. For example, the 2001 Doha Declaration on the TRIPS Agreement and Public Health clarified that countries had the right to choose their own grounds for issuing compulsory licenses and that they could prioritize public health and access to medicines for all.
In the years following, compulsory licensing mechanisms became more commonly employed. That effort seemed to wane after the creation of the Medicines Patent Pool (MPP) in 2010. Under the MPP, voluntary licenses would be issued to a small group of firms for manufacture and export to a fixed list of countries authorized by the originator pharmaceutical firm – a list that frequently excluded many commercially attractive upper-middle-income countries (UMICs), since originator firms often sought to limit competition from generics in those markets so they alone could reap commercial returns.
Even during the COVID-19 pandemic, countries leaned primarily on voluntary licensing to expand manufacturing of diagnostics, vaccines and, eventually, therapeutics. Paradoxically, the richest countries were among the few who did rush to use their laws to override patent rights to address pandemic needs. Meanwhile, a growing number of countries, led by South Africa and India, pushed for a waiver of the TRIPS Agreement constraints to make it easier to override patent rights more generally.
Rationale for the study
Given their routine exclusion from voluntary licenses and additional obstacles to accessing medicines that many middle-income countries experience, members of the Working Group had previously recommended further research to understand why compulsory licensing is underutilized. The research published in our report sought to explore whether the laws on the books for these countries could make granting compulsory licenses more difficult than necessary, or whether they were as expansive as they could be under the constraints of the TRIPS Agreement.
The study examined the extent to which countries typically excluded from voluntary licenses have incorporated TRIPS-compliant flexibilities into their domestic compulsory licensing laws in ways that make those laws as effective and easy to use as global rules allow. The countries assessed include Algeria, Argentina, China, Colombia, Ecuador, Jordan, Malaysia, Mexico, Panama, Peru, Philippines, Romania, Thailand, Turkey and Ukraine, all of which have been excluded from MPP voluntary licenses in the past.
Diverse adoption of TRIPS flexibilities
In order to compare laws across countries, the report divides the “best practices” for compulsory licensing legislation into three categories: (1) the breadth of the grounds allowed for issuing licenses, (2) the procedural flexibilities (measuring general ease-of-use for the compulsory licensing law) and (3) the scope of use (measuring the ability to use the license effectively for increased access to medicines in the licensing country and beyond). Although all 15 countries have compulsory licensing laws, they vary quite widely in how they adopt those rules.
Figure 1 provides a visual example of this diversity and highlights the varying range of reasons for granting compulsory licenses in different countries. The figure shows that Mexico (light blue) includes many different grounds for issuing emergency licenses (87.5 percent of the maximum, where the maximum is identified as the highest number of grounds in any study country) but does not allow these licenses to be granted at all as an anti-competitive remedy, nor for public interest purposes. Colombia (orange) by contrast includes a wide range of grounds within its public interest license (90 percent of the maximum) but fewer grounds for emergencies than Mexico. In this figure, the larger the area within a given shape, the more possibilities there are for countries to grant compulsory licenses, thus, more policy space.
Figure 1: Breadth of grounds for granting compulsory licenses in select Latin American countries
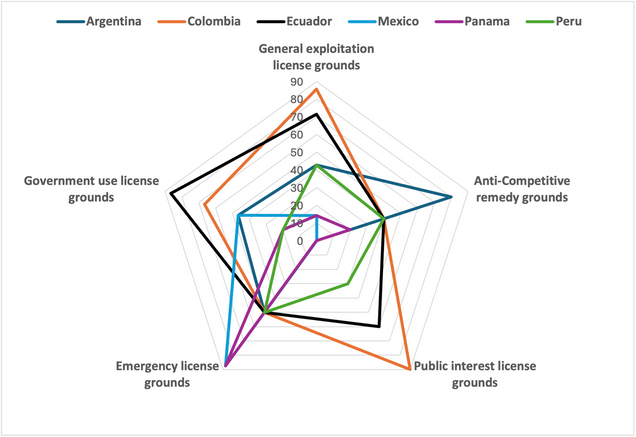
The report found similar levels of diversity among study countries in both procedural flexibilities and scope of use. Countries with a lot of flexibility built into their laws for one category of practices might have very little in another. Peru’s law (green), for example, has quite narrow allowable grounds for granting a license, and it was the only country in our study that did not have any reference to health emergencies or access to medicines as a ground for issuing licenses (see Table 5 in the report). Procedurally, however, Peru’s law is among the easiest to use to request and grant such a license (see Figure 2 in the report).
National legislation is only the beginning
Regardless of the flexibility and usability of a country’s compulsory licensing laws, there are many contextual factors beyond the law itself that influence whether they are actually used to issue licenses. To explore the extra-legal factors that play a role, the report includes two case studies: Thailand and Colombia. These case studies drive home the fact that, although expanding policy space in national laws can improve access to medicines, the successful issuance of licenses does not depend on the quality of legislation alone.
Due to the complexity of patents and trade secret landscapes, compulsory licensing can be limited by the need to access multiple related patents and undisclosed know-how that is held only by the original patent holder. Countries may lack the political will internally or experience political pressure externally such that granting a compulsory license is not politically feasible. Similarly, if the epidemiological need is not high enough in a specific country, there may not be broad-based support for a license. Sometimes regulatory requirements pose additional obstacles because they have not been harmonized across borders. Finally, even if all those hurdles have been overcome, a country may not on its own have sufficient technical and financial capacity to overcome market barriers. This last obstacle can be particularly important because most low- and middle-income countries have small domestic markets. They often lack large enough populations to be economically attractive to one or more generic manufacturers on their own.
EU regional compulsory licensing: An example to follow
Countries facing each of these obstacles will need to deploy a diverse set of policy solutions. One particularly salient policy recommendation made in the report is that middle-income countries should cooperate in establishing best practices within their laws and should collaborate to grant licenses to create aggregate markets and generate economies of scale for generic manufacturers. Although most large European countries do not face the same obstacles listed above, the EU Parliament has seen the value of cooperating at a regional level in a health crisis to aggregate demand and accelerate access. Low- and middle-income countries could adopt such a mechanism in their own regional and mega-regional integration agreements.
The African Continental Free Trade Agreement and Association of Southeast Asian Nations both have active negotiations taking place that could address the need for each region to develop a region-wide intellectual property policy and a region-wide compulsory licensing mechanism. By learning from the EU, they could starkly improve health outcomes for their member states and be better prepared for the next global health crisis.
Read the Report